

High Myopia Traction Maculopathy
<< Back to Cases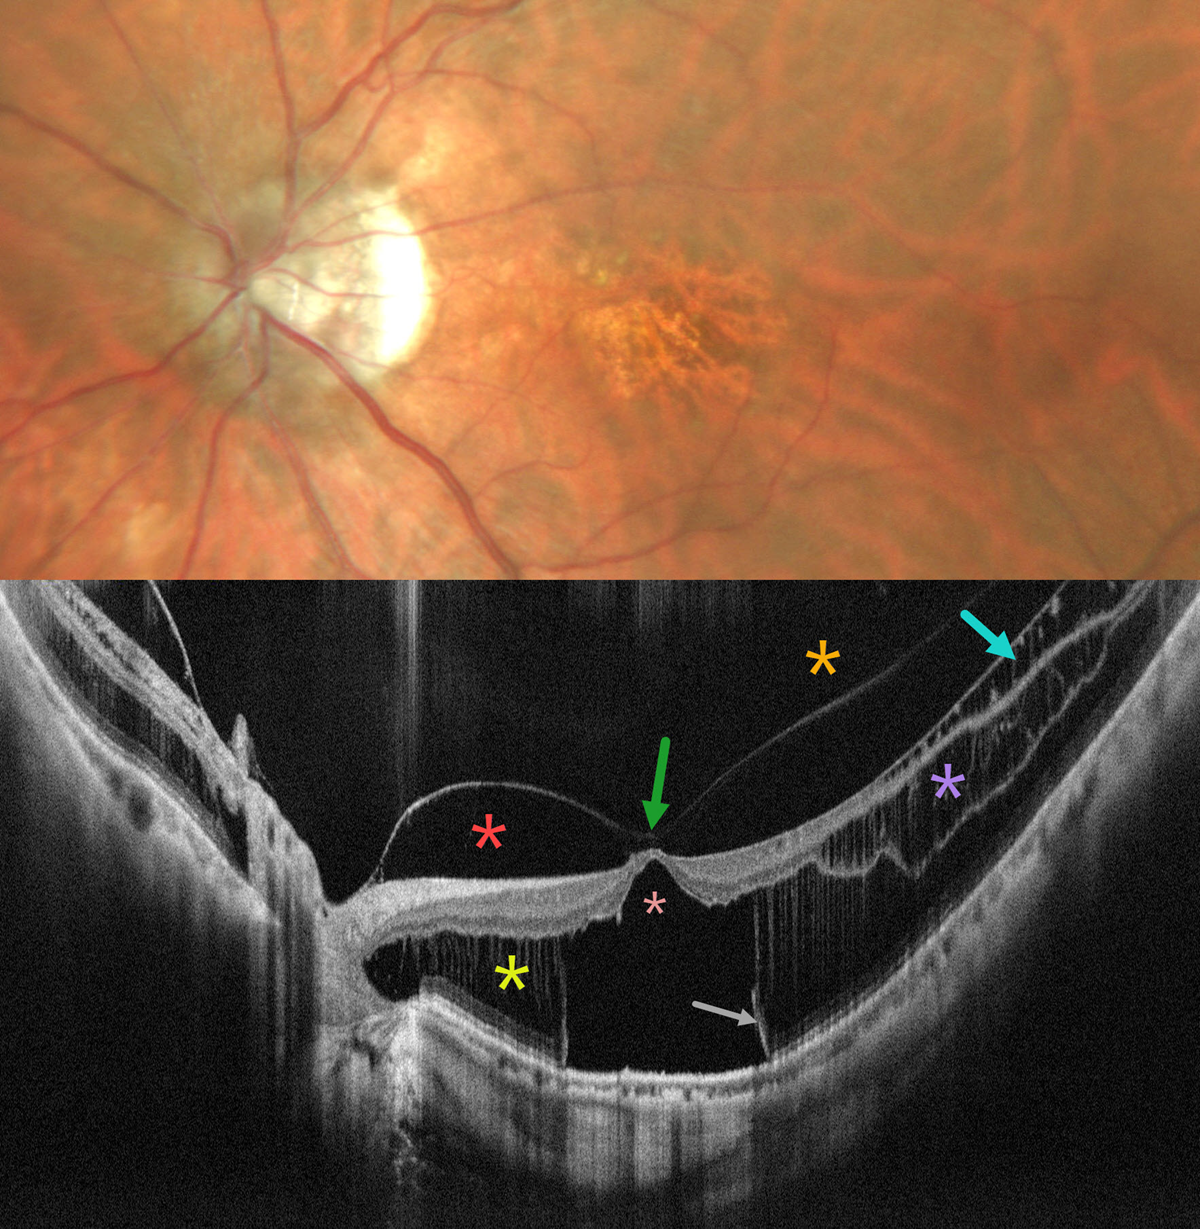
MYOPIC TRACTION MACULOPATHY
Malvika Singh, Akansha Sharma, Barbara Parolini and Manish Nagpal
Originally posted on @retina.rocks November 3, 2026
This 47YO highly myopic female presented with 1.5 years of decreased vision in her left eye. Vision was 20/80 OD and counting fingers OS.
Color photography is fairly unremarkable, with a tessellated choroid with highly visible choroidal vasculature, central macular pigmentary loss, and a tilted nerve temporal peripapillary atrophy. However, the OCT reveals a dramatically different and complex picture, mostly a myopic posterior staphyloma.
Both inner and outer nuclear layer schisis are noted. The central outer macula is absent deep to the outer plexiform layer, with an outer macular lamellar hole. Bare RPE is present at the base of this optically empty region, which is demarcated by near-vertical pillars of apparent ellipsoid zone. The vitreous is partially detached with a premacular bursa and remains attached to the nerve and fovea, creating focal vitreomacular traction (VMT). Finally, there is temporal ganglion cell layer schisis. The underlying choroid is diffusely thinned, particularly within the staphyloma.
Management of myopic traction maculopathy (MTM) is stage-dependent, ranging from observation in early asymptomatic disease to surgery for progressive or vision-threatening lesions. Surgery is indicated for progressive vision decline, foveal detachment, macular hole (MH), and/or macular hole rhegmatogenous retinal detachment (RRD).
Learning Points:
Two complementary surgical approaches include 1) pars plana vitrectomy (PPV, to relieve tangential traction) with internal limiting membrane peeling (often fovea-sparing to reduce the risk of iatrogenic MH) and gas tamponade and 2) macular buckling, which counteracts the perpendicular tractional force of the posterior staphyloma (Takahashi et al, Prog Retin Eye Res2026;110:101434 and Serhan et al, AJO 2025;270:25-34). The two may be combined in advanced cases such as macular hole-related RRD.
Our patient’s pathology appears to be purely caused by staphylomatous changes and, according to the Myopic Traction Maculopathy Staging System (MSS), has a Stage 3aO+ macular schisis detachment (Parolini et al, Eur J Ophthalmol 2021;31:1299-1312). Ripa et al reported 98% and 100% foveal and retinal anatomic improvement, respectively, in such eyes following macular buckling.

MYOPIC TRACTION MACULOPATHY
Barbara Parolini and Tommaso Pellegrino
Originally posted on @retina.rocks September 26, 2025
This 64YO female has a history of high myopia with posterior staphyloma. The axial length is 24.8 mm. Vision in the right eye has been deteriorating to 20/40.
Optos color RG imaging shows a posterior staphyloma, Type I (wide macula), in the right eye, which encircles the macula and disc. Ultra-widefield OCT (DreamOCT Intalight, 26 mm scan) shows a partial posterior vitreous detachment over the macula into the staphyloma with inner and outer retinal schisis within the staphyloma. There is no retinal detachment.
Learning Points:
Pathologic or high myopia is usually defined as a refractive error of at least -6 diopters with an axial length of at least 26.5 mm, so our patient technically is not a ‘high’ myope. 3D MRI imaging allows for a more nuanced definition and has shown that the ocular deformations can affect the entire eye, the equatorial, or just the posterior globe (Luo et al, JAMA Ophthalmology 2023;141:768-774). As defined by Luo et al, our patient has a posterior bulb-shaped globe. The ultra-widefield OCT is designed to image the entire posterior profile of the eye, which shows the geometry of our patient’s staphyloma.
The image also shows that myopic traction maculopathy (MTM) underlies a partial vitreous detachment. This confirms that the main cause of MTM is not the vitreous but the posterior staphyloma. Furthermore, when looking at the horizontal scan, the thickness of the retina (or, in other words, the severity of the schisis) is not evenly distributed into the staphyloma. It is more pronounced in the temporal side of the macula. The optic nerve pushes the sclera anteriorly, buckling the retina in that area and releasing the traction.
In the vertical scan, the schisis is uniformly distributed in the whole staphyloma. According to the ATN (atrophic, tractional, and neovascular) classification system for myopic maculopathy (Ruiz-Medrano et al, Progress Retinal Eye Research 2019;69:80-115), our patient has A1 (tessellated fundus only), T2 (inner + outer foveoschisis), and N0 (no myopic CNV). According to the myopic traction maculopathy staging system (MSS, Parolini et al, Ophthalmic Surg Lasers Imaging Retina 2023;54:153-157), our patient is affected by MTM in Stage 2a (predominantly outer macular schisis with no macular hole).


