World’s Largest Free Retina Image Gallery & Reference Library

Retina Rocks, the image bank of the Retina World Congress, is a free, open-source online image library whose mission is to help educate the world’s eye care providers about why the retina rocks!

Image Gallery   Over 51,000 multimodal images
Reference Library   Over 14,000 annotated citations from the major eye journals
Cases Atlas   Over 1,600 case studies organized by disease entity
Instagram   Access our Instagram feed @retina.rocks
Wall of Fame   Look here for the best submitted cases and images


Case of the Day

Have a comment or question about today's case? Go to your favorite social media platform to join the conversation!

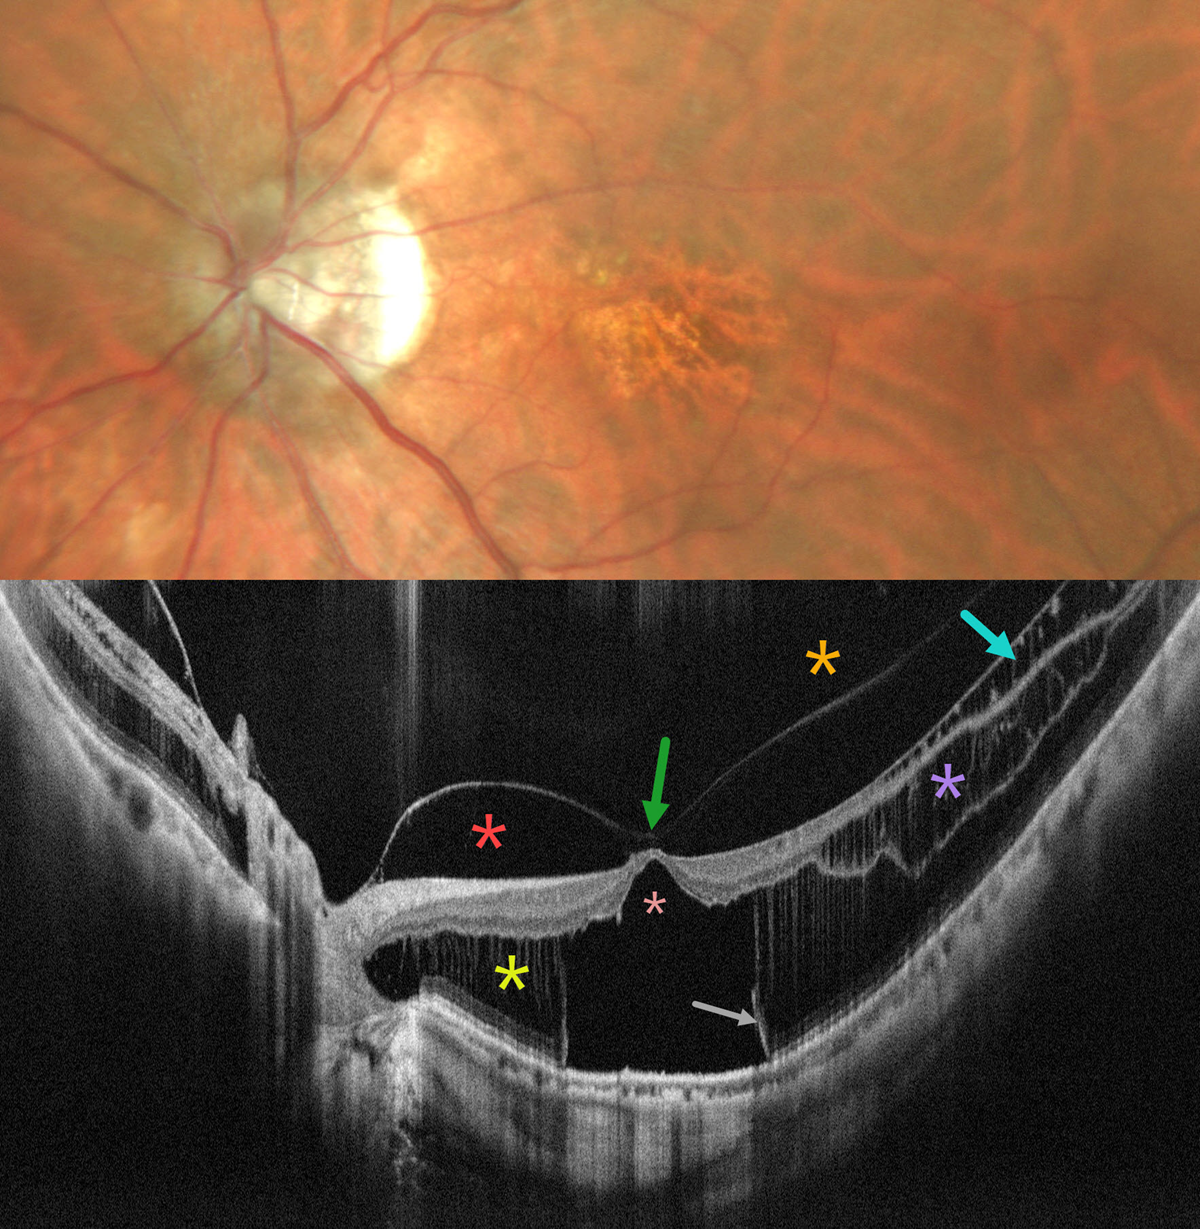
MYOPIC TRACTION MACULOPATHY

Malvika Singh, Akansha Sharma, Barbara Parolini and Manish Nagpal

This 47YO highly myopic female presented with 1.5 years of decreased vision in her left eye. Vision was 20/80 OD and counting fingers OS.

Color photography is fairly unremarkable, with a tessellated choroid with highly visible choroidal vasculature, central macular pigmentary loss, and a tilted nerve temporal peripapillary atrophy. However, the OCT reveals a dramatically different and complex picture, mostly a myopic posterior staphyloma.

Both inner and outer nuclear layer schisis are noted. The central outer macula is absent deep to the outer plexiform layer, with an outer macular lamellar hole. Bare RPE is present at the base of this optically empty region, which is demarcated by near-vertical pillars of apparent ellipsoid zone. The vitreous is partially detached with a premacular bursa and remains attached to the nerve and fovea, creating focal vitreomacular traction (VMT). Finally, there is temporal ganglion cell layer schisis. The underlying choroid is diffusely thinned, particularly within the staphyloma.

Management of myopic traction maculopathy (MTM) is stage-dependent, ranging from observation in early asymptomatic disease to surgery for progressive or vision-threatening lesions. Surgery is indicated for progressive vision decline, foveal detachment, macular hole (MH), and/or macular hole rhegmatogenous retinal detachment (RRD).

Learning Points:
Two complementary surgical approaches include 1) pars plana vitrectomy (PPV, to relieve tangential traction) with internal limiting membrane peeling (often fovea-sparing to reduce the risk of iatrogenic MH) and gas tamponade and 2) macular buckling, which counteracts the perpendicular tractional force of the posterior staphyloma (Takahashi et al, Prog Retin Eye Res2026;110:101434 and Serhan et al, AJO 2025;270:25-34). The two may be combined in advanced cases such as macular hole-related RRD.

Our patient’s pathology appears to be purely caused by staphylomatous changes and, according to the Myopic Traction Maculopathy Staging System (MSS), has a Stage 3aO+ macular schisis detachment (Parolini et al, Eur J Ophthalmol 2021;31:1299-1312). Ripa et al reported 98% and 100% foveal and retinal anatomic improvement, respectively, in such eyes following macular buckling.

Article of the Day

Long-term follow-up and outcomes of a Diabetic Eye Screening Programme in patients aged 80 with no diabetic eye disease at baseline: should we be routinely screening this cohort?

Paris A, Webster L, Eleftheriadis H, Mann S

Eye (Lond). 2026 Oct;40(14):2187-2192. doi: 10.1038/s41433-026-04699-4.

Summary

Diabetic retinopathy screening in 80YO or older: 0.11% needed DME treatment, and no PDR identified. Suggests routine screening for this population should be reconsidered — Retrospective, 3599 patients

Abstract

Background/objectives: It remains unclear whether routine annual diabetic eye screening is still warranted for individuals aged 80 and over who show no signs of retinopathy at baseline. This study aimed to determine the incidence of referable diabetic retinopathy (DR) or diabetic maculopathy in individuals aged 80 years and older with no retinopathy at baseline in the South East London NHS Diabetic Eye Screening Programme (DESP), and to estimate the proportion requiring treatment.

Subject/methods: Data from the South East London DESP were linked with Hospital Eye Service (HES) records from 2009 to 2025. Individuals aged 80 years during 2009-2014 with no diabetic retinopathy or maculopathy (R0M0) at baseline and at least five years of follow-up were included. Screening and hospital data were analysed to determine referrals, diagnoses and treatments.

Results: Of 3599 eligible participants, 3258 (90.5%) had no referable diabetic retinopathy or diabetic maculopathy at final screening. In total, 532 (14.8%) were referred to HES, mainly for non-diabetic causes (56.6%). Referrals for sight-threatening diabetic retinopathy accounted for 89 cases (2.5%), and only four individuals (0.11%) required treatment, all for diabetic macular oedema. No cases of proliferative diabetic retinopathy were identified.

Conclusions: Among people aged 80 years and older without diabetic retinopathy at baseline, the incidence of sight-threatening disease and treatment need were extremely low. Routine DESP recall in this population may offer limited clinical benefit and should be reconsidered within a risk-stratified screening framework.

Download Article

Affiliate Societies

Retina Rocks